What is the difference between concierge medicine and an executive health program?
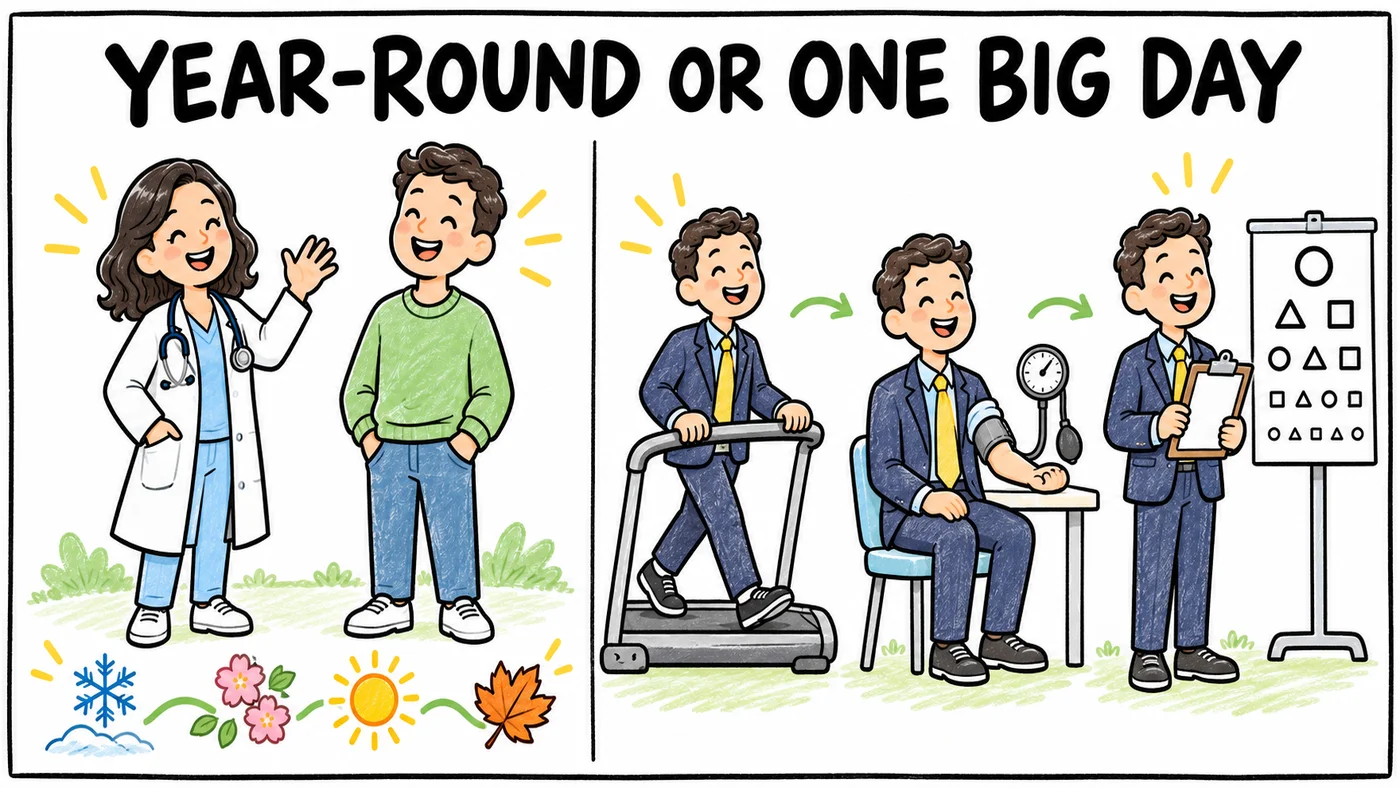
Concierge medicine is an ongoing relationship with a primary care physician who charges a membership fee for extra access, such as same-day appointments and phone access around the clock, and who often still bills insurance for covered visits. An executive health program is usually a one-day, in-depth checkup at a hospital or health system, with a physician exam, lab work, imaging, heart and fitness testing and lifestyle consults, and health systems sell it to employers for their leaders as well as to individuals. Concierge care gives you a doctor all year, while an executive physical gives you a very thorough snapshot once a year and then hands the findings back to whoever provides your ongoing care. Direct primary care (DPC) sits closer to concierge care, as a year-round relationship, but it is paid for with a monthly fee and no insurance billing.
This guide is written for physicians and DPC owners who hear these terms from patients and employers, and for the patients and benefits leaders asking the questions. It explains how each model works and how the tax rules treat them. It is not legal, tax or financial advice, so the tax points below are a starting place for a conversation with a CPA, a benefits attorney or a broker.
Concierge, executive health and DPC at a glance
The three models can look alike from the outside, since each charges something on top of, or instead of, insurance. They differ in how long the relationship lasts, who usually pays and whether insurance is billed.
| Concierge medicine | Executive health program | Direct primary care | |
|---|---|---|---|
| What you get | An ongoing primary care doctor with extra access | A one-day, in-depth checkup with a written plan | An ongoing primary care doctor with direct access |
| How long it lasts | All year, renewed each year | Usually one day, often repeated yearly | All year, month to month |
| Who pays | The patient pays the membership fee | An employer or the individual | The patient, a family or an employer |
| How the fee is charged | Often an annual membership fee | A per-exam fee | A monthly membership fee |
| Insurance billing | Often bills insurance for covered visits | Depends on the program and the tests | No insurance billing for what the fee covers |
| Who handles follow-up | The concierge doctor | Often the patient's own doctor, sometimes the program | The DPC doctor |
What is concierge medicine?
Concierge medicine is a primary care practice that charges patients a membership fee for extra access and time, on top of whatever insurance pays. The U.S. Government Accountability Office defined it as "an approach to medical practice in which physicians charge their patients a membership fee" in its report on concierge care, the most detailed federal study of the model we found.
The report is old, so read it with its dates in mind. GAO surveyed concierge physicians in the fall of 2004, got answers from 112 of the 146 it identified, and published on August 12, 2005. Nearly all of the respondents practiced primary care, and the features they reported most were same-day or next-day appointments for nonurgent care, 24-hour phone access and periodic preventive exams.
In that survey, annual membership fees ranged from $60 to $15,000 a year, and about half of the physicians reported fees of $1,500 to $1,999. Those are fees from two decades ago, so for what is and isn't known about current fees, see our guide to concierge medicine pricing.
The part of GAO's findings that still describes the model well is the billing. About three-fourths of the physicians who answered said they billed patients' health insurance for covered services, and almost all of those billed Medicare too, according to the full GAO report. The AAFP draws the same line today, describing concierge practices as ones that may bill a patient's insurance for covered services and often charge higher annual fees, while DPC practices rely on patient fees and don't take part in payer programs.
How concierge practices handle Medicare patients
Medicare.gov describes concierge care as a doctor charging a membership fee before they'll see you, and says plainly that Medicare doesn't cover those fees. Doctors who accept assignment can't charge extra for Medicare-covered services, but any Medicare doctor can charge for items and services Medicare doesn't cover.
That is why concierge contracts get careful legal review. In a March 31, 2004 alert, the HHS Office of Inspector General reminded participating physicians that asking Medicare patients to pay again for services Medicare already covers, beyond deductibles and coinsurance, can bring civil money penalties and exclusion. Physicians weighing a membership model with Medicare patients will also want our guides to opting out of Medicare for DPC and DPC for seniors on Medicare.
What does an executive physical include?
An executive physical is a long, structured checkup that a health system packs into a single day, so a busy person gets through tests that might otherwise take weeks of appointments. We read the public executive physical pages of three health systems on November 10, 2026, and the descriptions shared a clear shape, even though the exact tests differ by program and by patient.
The common pieces were these:
- A pre-visit and a full physician exam. A medical history review and physical exam, sometimes with a phone or video call with the physician before the visit day.
- Lab work. A full blood chemistry panel and urinalysis, with tests that differ for men and women, such as a PSA test for men in one program.
- Heart and fitness testing. An EKG, and in one program a treadmill stress test with an estimate of aerobic fitness, along with body composition testing.
- Imaging. In one program, a chest X-ray, ultrasounds of the neck and leg arteries and a coronary calcium CT scan from age 45.
- Lifestyle consults. Sessions with a dietitian and an exercise physiologist.
- Other screenings and specialists. Skin checks, hearing tests and consults with specialists such as cardiology or gastroenterology, sometimes as optional add-ons.
- Results and a plan. A review of results with the lead physician, recommendations and a risk-reduction plan, results in the patient portal and follow-up messages afterward.
Two of the three pages also spoke directly to employers. One said its evaluation is customized by the patient's employer, and another offered corporate enrollment along with ongoing primary care. That matters, because an executive physical on its own is not a primary care relationship. Someone still has to act on what the day finds.
Are all those tests recommended?
Not for everyone. The U.S. Preventive Services Task Force recommends against screening adults at low risk of heart disease with a resting or exercise ECG (a grade D recommendation from 2018), and says the evidence is insufficient to judge that screening for adults at intermediate or high risk. An executive physical can still be the right choice for a given person, especially one with symptoms or risk factors, but the number of tests is not a measure of how much good it does. Our guide to annual physicals and preventive care in DPC goes through what the evidence supports and what it doesn't.
Who pays for concierge care and executive physicals?
In concierge medicine, the patient usually pays the membership fee, and insurance or Medicare pays for the covered visits. Medicare does not pay the fee. For an executive physical, Medicare covers a yearly "Wellness" visit, which Medicare.gov says "isn't a routine physical exam," and a patient may have to pay the full amount for tests Medicare doesn't cover. Some employers do pay concierge fees for executives, but we found no federal or peer-reviewed data on how often that happens.
Executive physicals run the other way. The program pages we read describe employer contracts and corporate enrollment, and individuals can also book on their own. We found no national data on how many executive physicals are paid by employers versus individuals, or on what they typically cost, so we don't give a figure here. If you are comparing programs, ask each one for its price, what it bills to insurance, if anything, and what happens after the visit day.
How is an executive physical taxed when an employer pays?
This is where the two models part ways most clearly for employers, and it is a topic for a benefits attorney or CPA before a program is set up. Here is how the federal rules read.
IRS Publication 15-B, the employer's guide to fringe benefits for 2026, says employers can generally exclude the value of accident or health benefits they provide from an employee's wages. An executive physical paid for as a health benefit starts from that general rule.
The complication is Internal Revenue Code section 105(h). Under 26 CFR 1.105-11, a self-insured medical reimbursement plan, meaning a separate written plan that reimburses employees' medical expenses other than through an insurance policy, has to pass eligibility and benefit tests. If it favors highly compensated individuals, part or all of what it pays them becomes an "excess reimbursement" that they can't exclude from income.
Publication 15-B defines a highly compensated employee for this purpose as one of the five highest paid officers, an employee who owns more than 10% of the employer's stock, or an employee among the highest paid 25% of all employees, and it says those amounts are still excluded from the wages subject to withholding and to Social Security, Medicare and FUTA taxes.
A plan that pays only for executives would usually raise that issue, which is why the regulation's exception for diagnostic procedures matters so much here. Under paragraph (g) of the same regulation, reimbursements for medical diagnostic procedures for an employee, though not for a dependent, are left out of the discrimination tests. The regulation names "routine medical examinations, blood tests, and X-rays," and sets three limits:
- The procedures can't be for the treatment, cure or testing of a known illness or disability, or for a physical injury, complaint or specific symptom.
- They can't be activities for exercise, fitness, nutrition, recreation or the general improvement of health, unless those are medical care, which can reach the fitness testing and dietitian or exercise consults described above.
- They have to be done at a facility that provides only medical and ancillary services.
The same paragraph covers travel to the exam, but not travel taken merely for the general improvement of health or in connection with a vacation. Publication 15-B also notes that a 2% shareholder of an S corporation isn't treated as an employee for this exclusion, which matters for owner-run businesses.
None of this tells an employer whether its own program is a self-insured plan, an insured benefit or something else, and plan design changes the answer. The regulation treats a plan as self-insured unless the reimbursement comes from an insurance policy or a similarly regulated prepaid arrangement. A program that pays for medical care for employees can also carry ERISA duties, which our guide to onsite employer clinics vs DPC walks through. An employer should have its benefits counsel review the design before anyone books an exam.
What if you pay for an executive physical yourself?
IRS Publication 502, for 2025 returns, says you can include in medical expenses what you pay for an annual physical examination and diagnostic tests by a physician, and that you don't have to be ill at the time. You can deduct only the part of your medical expenses above 7.5% of your adjusted gross income, and only if you itemize. Membership fees raise their own questions, which our guide to whether a concierge or DPC membership is tax deductible covers.
Can you use an HSA for concierge, executive health or DPC fees?
Direct primary care now has its own rule in the tax code, and the other two don't fit it neatly. Since January 1, 2026, 26 U.S.C. 223(c)(1)(E) says a direct primary care service arrangement isn't treated as a health plan that would disqualify someone from an HSA, and section 223(d)(2)(C)(v) lets an HSA pay their fees. The statute defines one as medical care "consisting solely of primary care services provided by primary care practitioners," where "the sole compensation for such care is a fixed periodic fee," and it leaves out procedures needing general anesthesia, prescription drugs other than vaccines and lab services not typically done in an ambulatory primary care setting.
The fee also has a monthly cap. IRS Rev. Proc. 2026-24 keeps it at $150 a month for one person and $300 for an arrangement covering more than one person in 2027.
Read against that definition, a concierge practice that also bills insurance for the same care doesn't qualify: IRS Notice 2026-5 says an arrangement that "bills separately for those items and services (through insurance or otherwise)" is not a direct primary care service arrangement. An executive physical doesn't need the DPC rule. An HSA can pay qualified medical expenses, which Publication 969 defines as medical care under section 213(d), and Publication 502 counts an annual physical examination and diagnostic tests by a physician, though not extras that are merely for general health, and not an exam your employer already paid for. We found no IRS guidance aimed at concierge retainers, so ask a CPA before paying one from an HSA, and ask an executive health program for an itemized bill. Our DPC HSA rules guide has the full detail on the DPC side.
How does direct primary care compare?
Direct primary care shares concierge medicine's promise of time and access, but it is built differently. The AAFP describes DPC as an alternative to fee-for-service insurance billing, where patients pay a monthly, quarterly or annual fee that covers most primary care services, and it describes DPC fees as low and monthly and concierge fees as often higher and annual. For current numbers, our DPC pricing report shows what practices publish, and our guide to DPC vs concierge medicine compares the two in more depth.
Compared with an executive physical, DPC is the relationship rather than the event. A DPC physician can order the screening tests that fit a patient's risk, follow up on what they find and stay reachable by phone and text in between, while the executive physical's report still needs someone to act on it. The two aren't rivals for every patient. A leader with an employer-paid executive physical can still have a DPC doctor who reads the report and carries the plan forward through the year.
What this means for DPC practices that sell to employers
An employer that already pays for executive physicals has shown that it values preventive care and quick access for at least some of its people. That makes it a natural conversation for a DPC practice, because a monthly membership can extend year-round access to the rest of the workforce, and to families, without a one-day program for each person. Our guides to selling DPC to employers and DPC for small businesses cover how those contracts work, and the tax and plan questions above belong with the employer's own advisors.
When those contracts grow, a lot of the work sits between systems. Enrollment lists need to match billing, new members need a welcome and a first visit, and results from outside checkups need to reach the right person and turn into a follow-up. Tabflows is a dedicated tech team that connects the tools a practice already uses, such as the EHR, billing and messaging, so follow-ups, tasks and patient context live in one place. Roster matching and new-member onboarding are workflows our team builds on request.
Questions to ask before choosing
A few questions sort out the three models quickly:
- Do I need a doctor all year, or a deep look once a year? Concierge care and DPC are relationships, and an executive physical is a single day.
- Who will act on the results? If the answer is "my regular doctor," make sure that doctor will get the report and has time to go through it.
- Does the practice bill insurance? Concierge practices often do, and DPC practices don't for what the fee covers, which changes what you pay and how HSA rules apply.
- For an employer, is this a self-insured plan, and who is it for? A program limited to executives raises section 105(h) questions that counsel should review.
- For patients on Medicare, what does the fee cover? A concierge fee can't be a second charge for services Medicare already pays for.
The short version
Concierge medicine is a year-round primary care relationship with a membership fee and, often, insurance billing. An executive health program is a one-day, test-heavy checkup that health systems sell to employers and individuals, and its value depends on someone acting on the results. Federal rules treat an employer-paid executive physical as a generally tax-free health benefit, with section 105(h) and its diagnostic procedure exception to check when the plan favors highly paid people. Direct primary care offers the year-round relationship for a monthly fee without insurance billing, and it is the only one of the three with its own HSA rule. For anything that turns on tax or plan design, bring in a CPA, a benefits attorney or a broker, and if you are building a membership practice of your own, start with our guide to starting a DPC practice.
FAQs
What is the difference between concierge medicine and an executive health program?
Concierge medicine is an ongoing relationship with a primary care physician who charges a membership fee for extra access, such as same-day visits and phone access around the clock, and who often still bills insurance for covered visits. An executive health program is usually a one-day, in-depth checkup at a health system, with a physician exam, lab work, imaging, fitness and heart testing and specialist or lifestyle consults, sold both to employers for their leaders and to individuals. Concierge care is a year-round doctor, while an executive physical is an annual snapshot that sends its findings back to whoever provides your ongoing care.
Does Medicare pay for concierge medicine or an executive physical?
Medicare does not cover concierge membership fees, according to Medicare.gov. A concierge physician who stays in Medicare cannot use the membership fee to charge extra for services Medicare already pays for, a point the HHS Office of Inspector General made in a March 31, 2004 alert. Medicare covers its own yearly wellness visit and listed preventive services, and tests in an executive physical beyond those may fall to the employer or the patient, so check with the program before booking.
Is an executive physical a taxable benefit when an employer pays for it?
Generally not, because IRS Publication 15-B says employers can generally exclude accident and health benefits from an employee's wages. The catch is a self-insured medical reimbursement plan that favors highly compensated employees, where Internal Revenue Code section 105(h) can make part of a highly compensated person's reimbursement taxable. The Treasury regulation at 26 CFR 1.105-11(g) leaves medical diagnostic procedures for the employee, such as routine exams, blood tests and X-rays, out of that test, as long as they are not for a known illness or a specific symptom, are not exercise, fitness, nutrition or general-health activities, and are done at a facility that provides only medical and ancillary services. Dependents' exams do not get that treatment. An employer should have its benefits counsel or CPA review the plan's design.
Can I deduct an executive physical I pay for myself?
Possibly. IRS Publication 502, for 2025 returns, says you can include the cost of an annual physical examination and diagnostic tests by a physician in medical expenses, and that you don't have to be ill at the time. You can only deduct medical expenses above 7.5% of your adjusted gross income, and only if you itemize on Schedule A. Travel taken mainly for general health improvement or a vacation is a different matter, so ask a CPA about anything beyond the exam itself.
Can I pay a concierge or executive health fee from an HSA?
The tax code now lets people with an HSA have a direct primary care service arrangement, defined as primary care paid for only by a fixed periodic fee, with a monthly cap that IRS Rev. Proc. 2026-24 keeps at $150 for one person and $300 for more than one in 2027. IRS Notice 2026-5 says an arrangement that also bills insurance for the care does not qualify, which leaves out a concierge practice that bills insurance. An executive physical you pay for yourself is a different case: an HSA can pay qualified medical expenses, and IRS Publication 502 counts an annual physical and diagnostic tests by a physician, though not general-health extras or an exam your employer paid for. Ask a CPA before paying a concierge retainer from an HSA.
How is direct primary care different from concierge medicine and executive health?
Direct primary care is a monthly membership that covers primary care with no insurance billing, according to the AAFP, which describes DPC fees as low and monthly and concierge fees as often higher and annual. Unlike an executive physical, DPC is a year-round relationship with your own doctor, and unlike concierge care, the practice does not bill insurance for the visits the fee covers. Members can pair a DPC membership with insurance for specialists, hospital care and emergencies.